中国临床药理学与治疗学 ›› 2026, Vol. 31 ›› Issue (9): 1221-1230.doi: 10.12092/j.issn.1009-2501.2026.09.008
• 临床药理学 • 上一篇
姜俞濛1( ), 李建中1, 杭永付2, 杨友静3, 陶莎莎3, 胡坤1, 徐德宇1, 卢国元1,*()
收稿日期:2025-07-04
修回日期:2025-12-15
出版日期:2026-09-26
发布日期:2026-10-08
通讯作者:
卢国元
E-mail:18151820813@163.com;sdfyylgy@163.com
作者简介:姜俞濛,女,硕士研究生,住院医师,研究方向:血药浓度影响因素。E-mail:基金资助:
Yumeng JIANG1(), Jianzhong LI1, Yongfu HANG2, Youjing YANG3, Shasha TAO3, Kun HU1, Deyu XU1, Guoyuan LU1,*()
Received:2025-07-04
Revised:2025-12-15
Online:2026-09-26
Published:2026-10-08
Contact:
Guoyuan LU
E-mail:18151820813@163.com;sdfyylgy@163.com
摘要:
目的: 分析腹膜透析相关性腹膜炎(peritoneal dialysis-related peritonitis,PDRP)患者腹腔内注射万古霉素后血药浓度的影响因素及与临床疗效的相关性。方法: 回顾性收集2021年1月至2024年8月苏州大学附属第一医院37例接受腹腔1 g万古霉素给药并监测血药浓度的PDRP患者临床资料,于第2次给药前0.5 h采血,测定首次血药浓度(谷浓度)。结果: 17例既往有腹膜炎感染史的PDRP患者首次血药浓度为11.22(9.46,11.93)μg/mL,显著高于20例无感染史的PDRP患者首次血药浓度[8.66(7.84,9.51)μg/mL(P<0.01)];Logistic回归分析提示腹膜炎感染史及给药间隔时长是首次血药浓度的独立影响因素(P<0.01);腹膜炎感染史在任何给药间隔下均能提高浓度,而给药间隔时间仅在无感染史患者中起明显作用;万古霉素治疗前、后,腹透液细胞成分及转阴天数在高浓度组与低浓度组差异无统计学意义(P>0.05);两组治疗后腹透液细胞成分和C反应蛋白(C-reactive protein,CRP)水平均较治疗前下降(P<0.05);高浓度组患者治疗后CRP水平较低浓度组患者高(P<0.05)。结论: 既往腹膜炎感染史和给药间隔时长可显著影响万古霉素首次血药浓度,但首次浓度水平对PDRP患者的临床疗效和转阴天数无显著影响。
中图分类号:
姜俞濛, 李建中, 杭永付, 杨友静, 陶莎莎, 胡坤, 徐德宇, 卢国元. 腹膜透析相关性腹膜炎患者的万古霉素首次血药浓度影响因素分析[J]. 中国临床药理学与治疗学, 2026, 31(9): 1221-1230.
Yumeng JIANG, Jianzhong LI, Yongfu HANG, Youjing YANG, Shasha TAO, Kun HU, Deyu XU, Guoyuan LU. Influencing factors of the first serum concentration of vancomycin in patients with peritoneal dialysis-related peritonitis[J]. Chinese Journal of Clinical Pharmacology and Therapeutics, 2026, 31(9): 1221-1230.
| Baseline characteristics | Dosing interval 48 h group | Dosing interval 72 h group | P |
| Dialysis duration (month) | 38(19,47) | 34(20,98) | 0.673 |
| Scr (μmol/L) | 946.45(783.80, | 0.126 | |
| CysC (mg/L) | 7.12(5.73,8.16) | 7.07(5.57,8.17) | 0.933 |
| Urea (mmol/L) | 24.00(14.85,26.30) | 22.40(16.90,29.20) | 0.768 |
| UA (μmol/L) | 351.00(274.80,464.00) | 327.60(279.28,401.13) | 0.399 |
| Urine volume (mL/24 h) | 0(0,865) | 0(0,125) | 0.418 |
| Kt/V | 1.56(1.44,1.73) | 1.68(1.37,1.88) | 0.593 |
| D/P | 0.68(0.62,0.75) | 0.69(0.61,0.75) | 0.994 |
| Peritoneal dialysate nucleated cell count (109/L) | 1.056(0.423,5.366) | 1.562(0.396,4.712) | 0.978 |
| Percentage of neutrophils in dialysate (%) | 86.0(79.4,90.3) | 83.7(74.4,90.1) | 0.663 |
| Peripheral blood WBC count (109/L) | 7.20(4.57,9.22) | 6.84(5.08,8.72) | 0.966 |
| Peripheral blood neutrophil percentage (%) | 75.4(68.4,83.8) | 78.2(67.0,83.5) | 0.536 |
| CRP (mg/L) | 12.93(10.06,50.34) | 27.38(14.25,49.55) | 0.126 |
| History of peritonitis infection (%) | 0.699 | ||
| No | 7(50.00) | 13(56.52) | |
| Yes | 7(50.00) | 10(43.48) |
表 1
Table 1 Comparison of renal function, peritoneal transport characteristics, and inflammatory status between the 48 h and 72 h dosing interval groups
| Baseline characteristics | Dosing interval 48 h group | Dosing interval 72 h group | P |
| Dialysis duration (month) | 38(19,47) | 34(20,98) | 0.673 |
| Scr (μmol/L) | 946.45(783.80, | 0.126 | |
| CysC (mg/L) | 7.12(5.73,8.16) | 7.07(5.57,8.17) | 0.933 |
| Urea (mmol/L) | 24.00(14.85,26.30) | 22.40(16.90,29.20) | 0.768 |
| UA (μmol/L) | 351.00(274.80,464.00) | 327.60(279.28,401.13) | 0.399 |
| Urine volume (mL/24 h) | 0(0,865) | 0(0,125) | 0.418 |
| Kt/V | 1.56(1.44,1.73) | 1.68(1.37,1.88) | 0.593 |
| D/P | 0.68(0.62,0.75) | 0.69(0.61,0.75) | 0.994 |
| Peritoneal dialysate nucleated cell count (109/L) | 1.056(0.423,5.366) | 1.562(0.396,4.712) | 0.978 |
| Percentage of neutrophils in dialysate (%) | 86.0(79.4,90.3) | 83.7(74.4,90.1) | 0.663 |
| Peripheral blood WBC count (109/L) | 7.20(4.57,9.22) | 6.84(5.08,8.72) | 0.966 |
| Peripheral blood neutrophil percentage (%) | 75.4(68.4,83.8) | 78.2(67.0,83.5) | 0.536 |
| CRP (mg/L) | 12.93(10.06,50.34) | 27.38(14.25,49.55) | 0.126 |
| History of peritonitis infection (%) | 0.699 | ||
| No | 7(50.00) | 13(56.52) | |
| Yes | 7(50.00) | 10(43.48) |
| Variable | Low-serum concentration group | High-serum concentration group | P |
| Sex (%) | 0.742 | ||
| Male | 12(57.14) | 10(62.50) | |
| Female | 9(42.86) | 6(37.50) | |
| Age (years) | 46(37,63) | 48(37,65) | 0.978 |
| BSA (m2) | 1.80(1.70,1.96) | 1.84(1.56,1.94) | 0.391 |
| Dialysis duration (month) | 38(19,61) | 34(22,94) | 0.649 |
| eGFR [mL/(min·1.73 m2)] | 5.00(4.05,5.60) | 4.40(3.60,6.10) | 0.934 |
| Scr (μmol/L) | 955.20(829.43, | 0.772 | |
| CysC (mg/L) | 7.27(5.37,8.22) | 7.12(6.27,7.44) | 0.610 |
| Urea (mmol/L) | 23.40(18.20,26.10) | 20.80(11.80,30.20) | 0.363 |
| UA (μmol/L) | 373.15(309.15,416.43) | 291.70(274.20,394.25) | 0.080 |
| ALT (U/L) | 12.70(9.43,19.00) | 8.50(6.80,15.20) | 0.045* |
| AST (U/L) | 12.20(10.30,17.20) | 11.50(9.20,20.40) | 0.895 |
| Urine volume (mL/24 h) | 0(0,200) | 0(0,365) | 0.678 |
| Kt/V | 1.62(1.40,1.88) | 1.57(1.34,1.73) | 0.581 |
| D/P | 0.70(0.61,0.76) | 0.68(0.60,0.73) | 0.349 |
| Peritoneal dialysate nucleated cell count (109/L) | 0.882(0.313,4.832) | 1.182(0.574,5.286) | 0.355 |
| Percentage of neutrophils in dialysate (%) | 85.0(75.0,92.0) | 86.0(76.4,88.4) | 0.783 |
| Peripheral blood WBC count (109/L) | 6.49(5.15,9.22) | 7.20(4.46,8.81) | 0.501 |
| Peripheral blood neutrophil percentage (%) | 79.8(68.2,83.8) | 73.1(63.6,82.5) | 0.214 |
| CRP (mg/L) | 26.16(12.08,85.2) | 15.68(12.45,43.80) | 0.155 |
| Bacterial species (%) | 0.500 | ||
| G+ | 11(52.38) | 11(68.75) | |
| G? | 10(47.62) | 5(31.25) | |
| Dosing interval (h) | 0.015* | ||
| 48 | 4(19.05) | 10(62.50) | |
| 72 | 17(80.95) | 6(37.50) | |
| History of peritonitis (%) | 0.022* | ||
| No | 15(71.43) | 5(31.25) | |
| Yes | 6(28.57) | 11(68.75) |
表 2
Table 2 Comparison of general information and laboratory indicators between the two groups
| Variable | Low-serum concentration group | High-serum concentration group | P |
| Sex (%) | 0.742 | ||
| Male | 12(57.14) | 10(62.50) | |
| Female | 9(42.86) | 6(37.50) | |
| Age (years) | 46(37,63) | 48(37,65) | 0.978 |
| BSA (m2) | 1.80(1.70,1.96) | 1.84(1.56,1.94) | 0.391 |
| Dialysis duration (month) | 38(19,61) | 34(22,94) | 0.649 |
| eGFR [mL/(min·1.73 m2)] | 5.00(4.05,5.60) | 4.40(3.60,6.10) | 0.934 |
| Scr (μmol/L) | 955.20(829.43, | 0.772 | |
| CysC (mg/L) | 7.27(5.37,8.22) | 7.12(6.27,7.44) | 0.610 |
| Urea (mmol/L) | 23.40(18.20,26.10) | 20.80(11.80,30.20) | 0.363 |
| UA (μmol/L) | 373.15(309.15,416.43) | 291.70(274.20,394.25) | 0.080 |
| ALT (U/L) | 12.70(9.43,19.00) | 8.50(6.80,15.20) | 0.045* |
| AST (U/L) | 12.20(10.30,17.20) | 11.50(9.20,20.40) | 0.895 |
| Urine volume (mL/24 h) | 0(0,200) | 0(0,365) | 0.678 |
| Kt/V | 1.62(1.40,1.88) | 1.57(1.34,1.73) | 0.581 |
| D/P | 0.70(0.61,0.76) | 0.68(0.60,0.73) | 0.349 |
| Peritoneal dialysate nucleated cell count (109/L) | 0.882(0.313,4.832) | 1.182(0.574,5.286) | 0.355 |
| Percentage of neutrophils in dialysate (%) | 85.0(75.0,92.0) | 86.0(76.4,88.4) | 0.783 |
| Peripheral blood WBC count (109/L) | 6.49(5.15,9.22) | 7.20(4.46,8.81) | 0.501 |
| Peripheral blood neutrophil percentage (%) | 79.8(68.2,83.8) | 73.1(63.6,82.5) | 0.214 |
| CRP (mg/L) | 26.16(12.08,85.2) | 15.68(12.45,43.80) | 0.155 |
| Bacterial species (%) | 0.500 | ||
| G+ | 11(52.38) | 11(68.75) | |
| G? | 10(47.62) | 5(31.25) | |
| Dosing interval (h) | 0.015* | ||
| 48 | 4(19.05) | 10(62.50) | |
| 72 | 17(80.95) | 6(37.50) | |
| History of peritonitis (%) | 0.022* | ||
| No | 15(71.43) | 5(31.25) | |
| Yes | 6(28.57) | 11(68.75) |
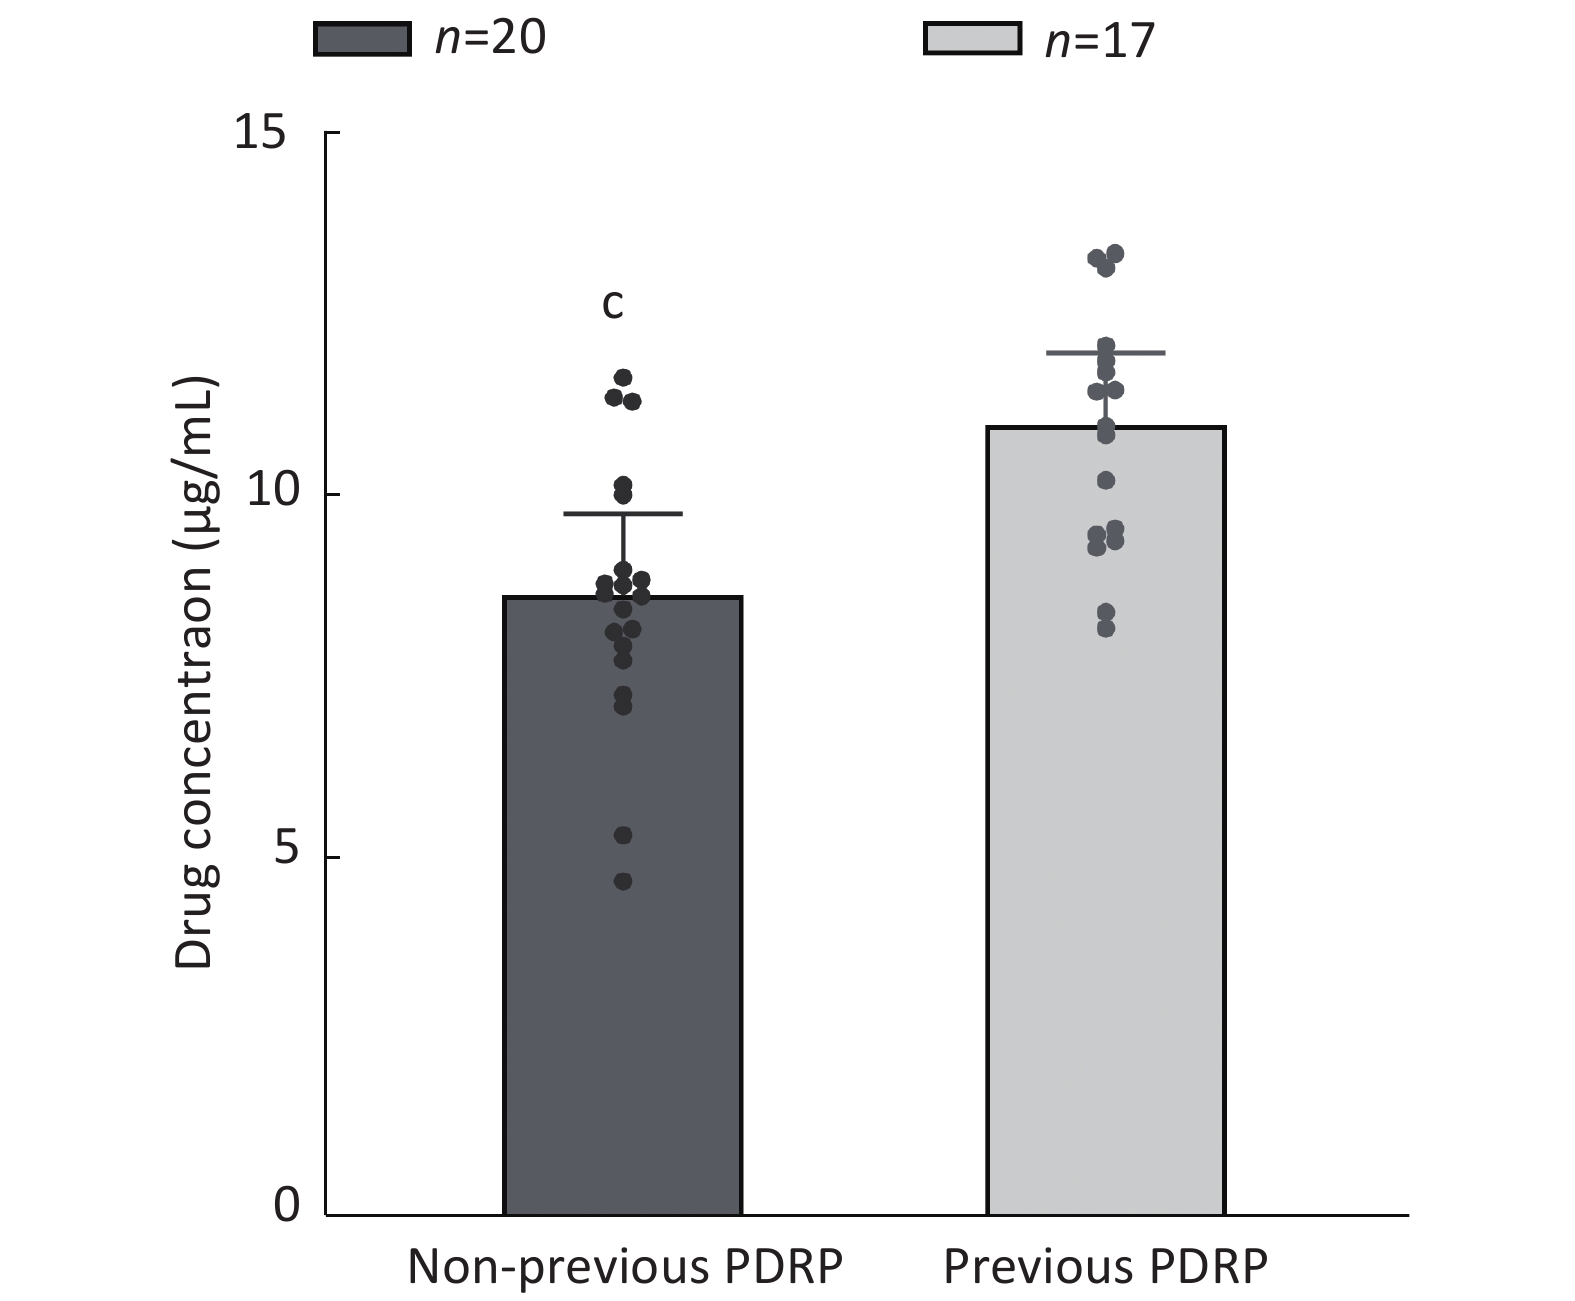
图 1 cP<0.01, compared with previous PDRP group.
Fig.1 Effect of a history of peritonitis infection on the first serum concentration ($\bar x $±s) cP<0.01, compared with previous PDRP group.
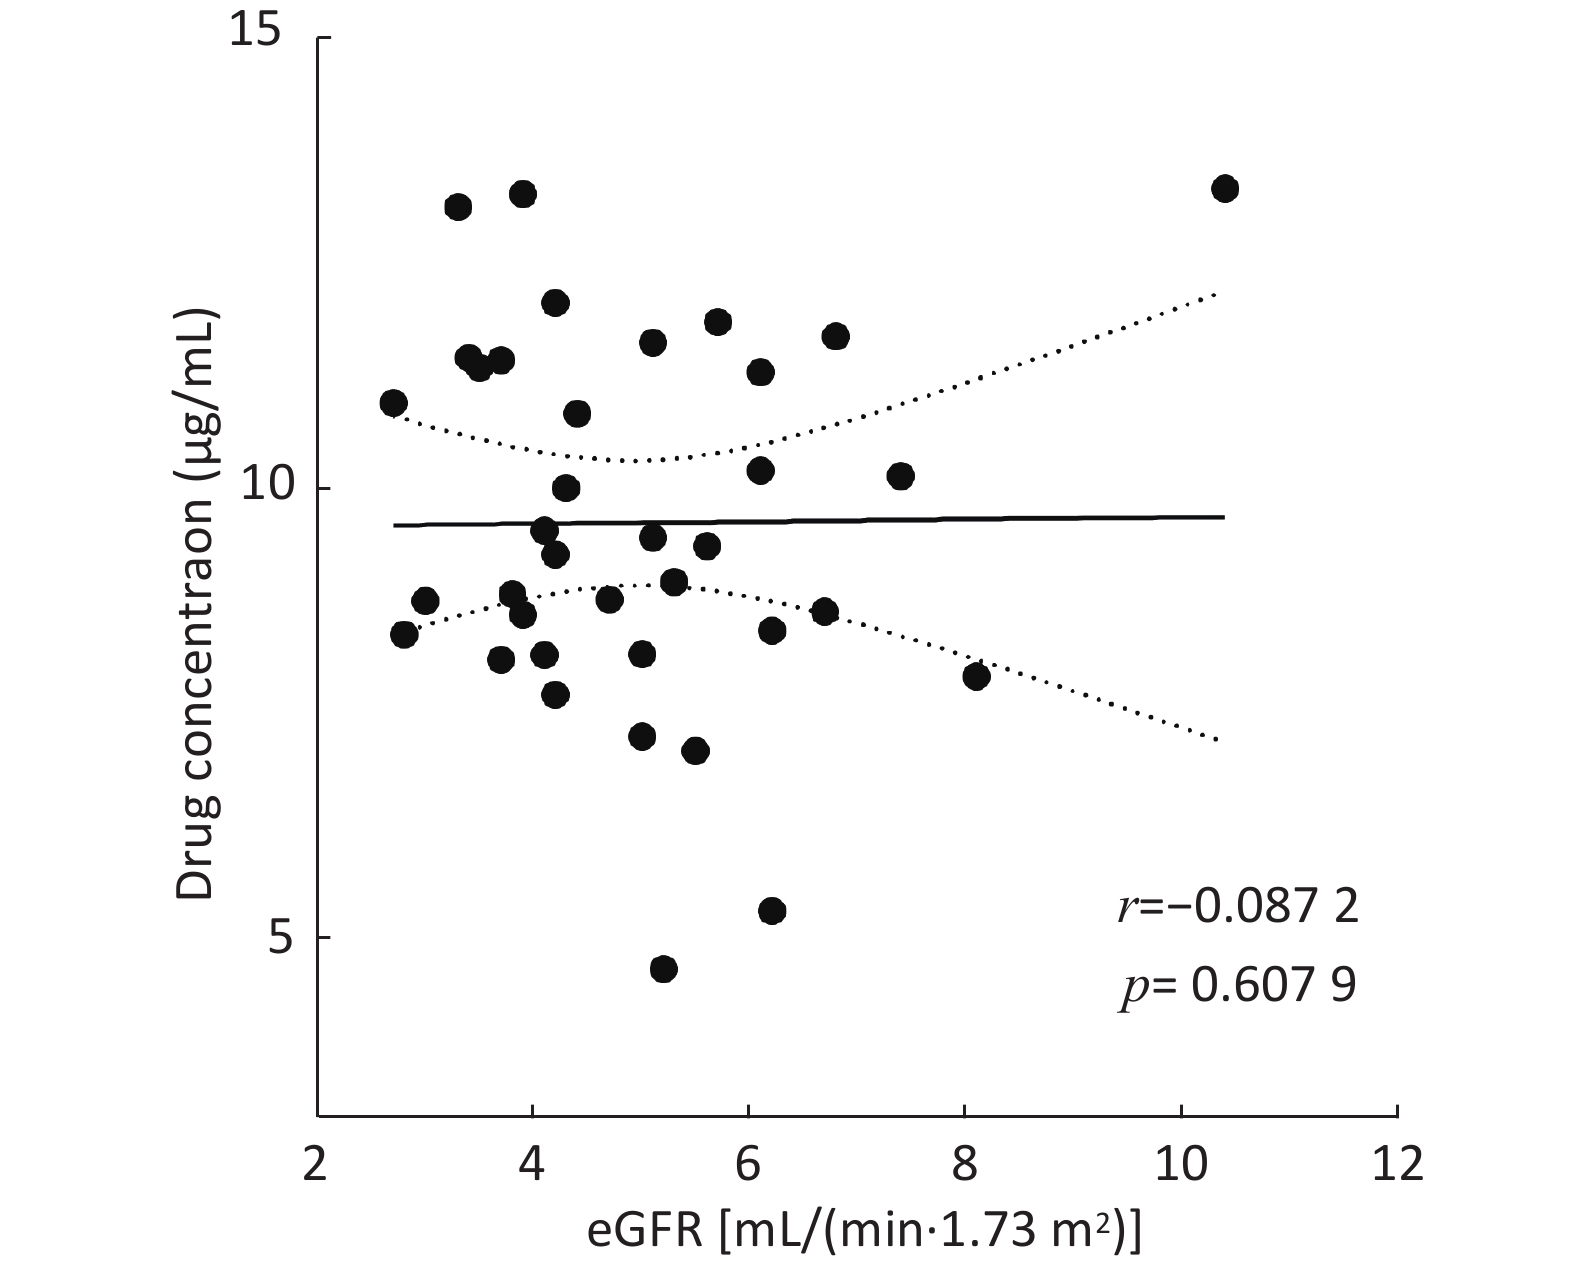
图 2
Fig.2 Correlation between eGFR and the first serum concentration of vancomycin
| Variable | Univariate logistic | Multivariate logistic | |||
| OR(95%CI) | P | OR(95%CI) | P | ||
| Sex (%) | |||||
| Male | Reference | ||||
| Female | 1.006(0.296,3.422) | 0.992 | |||
| Age (years) | 0.999(0.963,1.036) | 0.966 | |||
| BSA (m2) | 0.290(0.016,5.194) | 0.400 | |||
| Dialysis duration (month) | 1.003(0.992,1.015) | 0.597 | |||
| Scr (μmol/L) | 1.117(0.677,1.842) | 0.666 | |||
| CysC (mg/L) | 0.943(0.658,1.352) | 0.749 | |||
| Urea (mmol/L) | 0.977(0.921,1.036) | 0.440 | |||
| UA (μmol/L) | 0.996(0.990,1.001) | 0.114 | |||
| ALT (U/L) | 0.961(0.907,1.019) | 0.183 | |||
| AST (U/L) | 1.043(0.980,1.110) | 0.183 | |||
| Urine volume (mL/24 h) | 1.146(0.695,1.891) | 0.593 | |||
| Kt/V | 0.869(0.296,2.546) | 0.798 | |||
| D/P | 0.081(0.000,14.740) | 0.344 | |||
| Peritoneal dialysate nucleated cell count (109/L) | 0.959(0.834,1.102) | 0.552 | |||
| Percentage of neutrophils in dialysate (%) | 0.989(0.947,1.032) | 0.604 | |||
| Peripheral blood WBC count (109/L) | 1.059(0.907,1.237) | 0.470 | |||
| Peripheral blood neutrophil percentage (%) | 0.973(0.927,1.021) | 0.266 | |||
| CRP (mg/L) | 0.986(0.972,1.001) | 0.066 | 0.986(0.969,1.004) | 0.138 | |
| Bacterial species (%) | |||||
| G+ | Reference | ||||
| G? | 0.450(0.160,1.267) | 0.130 | |||
| Dosing interval (h) | |||||
| 48 | Reference | ||||
| 72 | 0.158(0.052,0.485) | 0.001 | 0.092(0.021,0.400) | 0.001 | |
| History of peritonitis (%) | |||||
| No | Reference | ||||
| Yes | 2.719(1.551,4.767) | 0.000 | 3.207(1.568,6.560) | 0.001 | |
表 3
Table 3 Logistic regression analysis of the influencing factors Vancomycin blood concentration
| Variable | Univariate logistic | Multivariate logistic | |||
| OR(95%CI) | P | OR(95%CI) | P | ||
| Sex (%) | |||||
| Male | Reference | ||||
| Female | 1.006(0.296,3.422) | 0.992 | |||
| Age (years) | 0.999(0.963,1.036) | 0.966 | |||
| BSA (m2) | 0.290(0.016,5.194) | 0.400 | |||
| Dialysis duration (month) | 1.003(0.992,1.015) | 0.597 | |||
| Scr (μmol/L) | 1.117(0.677,1.842) | 0.666 | |||
| CysC (mg/L) | 0.943(0.658,1.352) | 0.749 | |||
| Urea (mmol/L) | 0.977(0.921,1.036) | 0.440 | |||
| UA (μmol/L) | 0.996(0.990,1.001) | 0.114 | |||
| ALT (U/L) | 0.961(0.907,1.019) | 0.183 | |||
| AST (U/L) | 1.043(0.980,1.110) | 0.183 | |||
| Urine volume (mL/24 h) | 1.146(0.695,1.891) | 0.593 | |||
| Kt/V | 0.869(0.296,2.546) | 0.798 | |||
| D/P | 0.081(0.000,14.740) | 0.344 | |||
| Peritoneal dialysate nucleated cell count (109/L) | 0.959(0.834,1.102) | 0.552 | |||
| Percentage of neutrophils in dialysate (%) | 0.989(0.947,1.032) | 0.604 | |||
| Peripheral blood WBC count (109/L) | 1.059(0.907,1.237) | 0.470 | |||
| Peripheral blood neutrophil percentage (%) | 0.973(0.927,1.021) | 0.266 | |||
| CRP (mg/L) | 0.986(0.972,1.001) | 0.066 | 0.986(0.969,1.004) | 0.138 | |
| Bacterial species (%) | |||||
| G+ | Reference | ||||
| G? | 0.450(0.160,1.267) | 0.130 | |||
| Dosing interval (h) | |||||
| 48 | Reference | ||||
| 72 | 0.158(0.052,0.485) | 0.001 | 0.092(0.021,0.400) | 0.001 | |
| History of peritonitis (%) | |||||
| No | Reference | ||||
| Yes | 2.719(1.551,4.767) | 0.000 | 3.207(1.568,6.560) | 0.001 | |
| Variable | Unstandardized coefficients | Standardized coefficients | T | P | Collinearity diagnostics | ||
| B | Standard error | Beta | VIF | ||||
| CRP | ?0.002 | 0.001 | ?0.194 | ?1.881 | 0.065 | 1.039 | |
| Dosing interval | ?0.408 | 0.103 | ?0.400 | ?3.954 | <0.001 | 1.007 | |
| History of peritonitis | 0.383 | 0.103 | 0.393 | 3.815 | <0.001 | 1.044 | |
| R2 | 0.399 | ||||||
| Adjusted R2 | 0.369 | ||||||
表 4
Table 4 Multiple linear regression analysis of factors influencing the first serum concentration of vancomycin
| Variable | Unstandardized coefficients | Standardized coefficients | T | P | Collinearity diagnostics | ||
| B | Standard error | Beta | VIF | ||||
| CRP | ?0.002 | 0.001 | ?0.194 | ?1.881 | 0.065 | 1.039 | |
| Dosing interval | ?0.408 | 0.103 | ?0.400 | ?3.954 | <0.001 | 1.007 | |
| History of peritonitis | 0.383 | 0.103 | 0.393 | 3.815 | <0.001 | 1.044 | |
| R2 | 0.399 | ||||||
| Adjusted R2 | 0.369 | ||||||
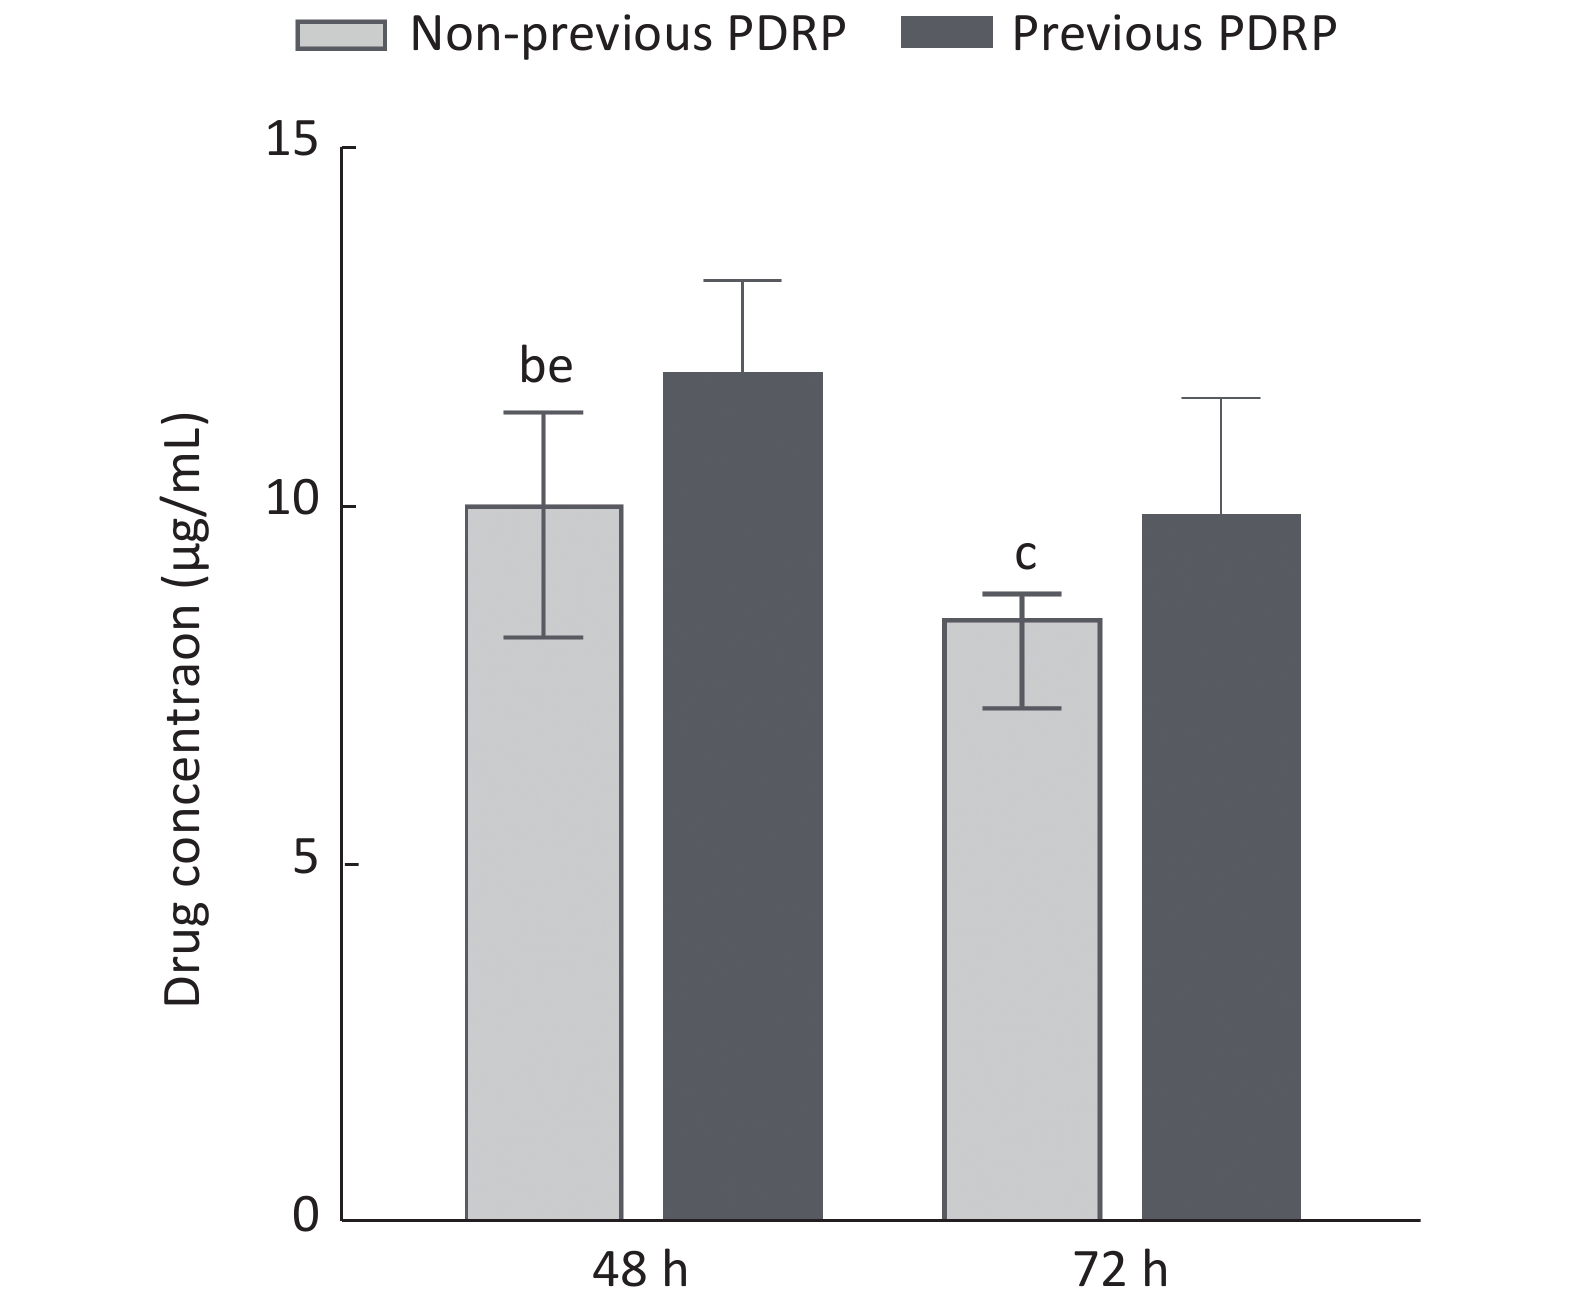
图 3
Fig.3 Stratified analysis of the impact of dosing interval and peritonitis history on the first serum concentration of vancomycin ($\bar x$±s) bP<0.05, cP<0.01, compared with previous PDRP; eP<0.05, compared with previous 72 h.
| Group | Peritoneal dialysate nucleated cell count (109/L) | P | Percentage of neutrophils in dialysate (%) | P | Days to negative conversion (d) | ||
| Before treatment | After treatment | Before treatment | After treatment | ||||
| Low-serum concentration group (n=11) | 0.396(0.226,6.238) | 0.020(0.007,0.026) | <0.001 | 80.7(75.0,90.9) | 10.0(6.4,22.7) | <0.001 | 5(2,8) |
| High-serum concentration group (n=11) | 1.182(0.574,6.285) | 0.011(0.004,0.43) | <0.001 | 86.4(78.0,87.2) | 9.3(0.0,18.0) | <0.001 | 5(3,7) |
| P | 0.158 | 0.641 | 0.821 | 0.373 | 0.798 | ||
表 5
Table 5 Comparison of cell components in peritoneal dialysis fluid before and after treatment in two groups
| Group | Peritoneal dialysate nucleated cell count (109/L) | P | Percentage of neutrophils in dialysate (%) | P | Days to negative conversion (d) | ||
| Before treatment | After treatment | Before treatment | After treatment | ||||
| Low-serum concentration group (n=11) | 0.396(0.226,6.238) | 0.020(0.007,0.026) | <0.001 | 80.7(75.0,90.9) | 10.0(6.4,22.7) | <0.001 | 5(2,8) |
| High-serum concentration group (n=11) | 1.182(0.574,6.285) | 0.011(0.004,0.43) | <0.001 | 86.4(78.0,87.2) | 9.3(0.0,18.0) | <0.001 | 5(3,7) |
| P | 0.158 | 0.641 | 0.821 | 0.373 | 0.798 | ||
| Group | CRP (mg/L) | P | |
| Before treatment | After treatment | ||
| Low-serum concentration group (n=11) | 20.41(15.60,44.55) | 4.89(3.00,7.70) | 0.001 |
| High-serum concentration group (n=11) | 16.44(12.93,43.80) | 6.56(5.59,7.72) | <0.001 |
| P | 0.598 | 0.045 | |
表 6
Table 6 Comparison of CRP before and after treatment in two groups
| Group | CRP (mg/L) | P | |
| Before treatment | After treatment | ||
| Low-serum concentration group (n=11) | 20.41(15.60,44.55) | 4.89(3.00,7.70) | 0.001 |
| High-serum concentration group (n=11) | 16.44(12.93,43.80) | 6.56(5.59,7.72) | <0.001 |
| P | 0.598 | 0.045 | |
| Author (Year) | Country | Case number | Dosage regimen | Serum concentration target | Main conclusions |
| Xie Jing et al.(2024)[ | China | 40 | 0.5 g vancomycin, administered qd, qod and q2d; Adjusting dosing regimens based on the serum concentration. | 15 μg/mL (ISPD guideline) | First serum concentration is difficult to achieve target; Clinical efficacy correlates with concentrations ≥10 μg/mL but not with 15 μg/mL. |
| Cai Le et al.(2021)[ | China | 24 | 1 g vancomycin, administered qd, qod and q2d. | 15 μg/mL (ISPD guideline) | First serum concentration is difficult to achieve target. |
| Hang Yong Fu et al.(2019)[ | China | 41 | 1 g vancomycin, administered q3d, q4d and q5d. | 15 μg/mL (ISPD guideline) | First serum concentration is difficult to achieve target. No correlation between serum concentration and clinical efficacy at 10 or 15 μg/mL. |
| Ma Ying et al.(2023)[ | China | 56 | 15 mg/kg vancomycin, administered on Day1, re-dose 0.5 g on Day3 if serum concentration <15 μg/mL; Adjusting dosing regimens based on the serum concentration on Day5. | 15 μg/mL (ISPD guideline) | No correlation between serum concentration and clinical efficacy. |
| Sarah Stevenson et al.(2015)[ | Australia | 34 | 30 mg/kg vancomycin (max 2.0 g), check serum concentration every 2-3 days and re-dose 30 mg/kg vancomycin (max 2.0 g) if <15 μg/mL. | 15 μg/mL (ISPD guideline) | No correlation between serum concentration and clinical efficacy. |
表 7
Table 7 Overview of domestic and international studies on vancomycin serum concentrations in peritoneal dialysis–related peritonitis
| Author (Year) | Country | Case number | Dosage regimen | Serum concentration target | Main conclusions |
| Xie Jing et al.(2024)[ | China | 40 | 0.5 g vancomycin, administered qd, qod and q2d; Adjusting dosing regimens based on the serum concentration. | 15 μg/mL (ISPD guideline) | First serum concentration is difficult to achieve target; Clinical efficacy correlates with concentrations ≥10 μg/mL but not with 15 μg/mL. |
| Cai Le et al.(2021)[ | China | 24 | 1 g vancomycin, administered qd, qod and q2d. | 15 μg/mL (ISPD guideline) | First serum concentration is difficult to achieve target. |
| Hang Yong Fu et al.(2019)[ | China | 41 | 1 g vancomycin, administered q3d, q4d and q5d. | 15 μg/mL (ISPD guideline) | First serum concentration is difficult to achieve target. No correlation between serum concentration and clinical efficacy at 10 or 15 μg/mL. |
| Ma Ying et al.(2023)[ | China | 56 | 15 mg/kg vancomycin, administered on Day1, re-dose 0.5 g on Day3 if serum concentration <15 μg/mL; Adjusting dosing regimens based on the serum concentration on Day5. | 15 μg/mL (ISPD guideline) | No correlation between serum concentration and clinical efficacy. |
| Sarah Stevenson et al.(2015)[ | Australia | 34 | 30 mg/kg vancomycin (max 2.0 g), check serum concentration every 2-3 days and re-dose 30 mg/kg vancomycin (max 2.0 g) if <15 μg/mL. | 15 μg/mL (ISPD guideline) | No correlation between serum concentration and clinical efficacy. |
| 1 |
Yu J, Zhu L, Ni J, et al. Technique failure in peritoneal dialysis-related peritonitis: risk factors and patient survival[J]. Ren Fail, 2023, 45 (1): 2205536.
doi: 10.1080/0886022X.2023.2205536 |
| 2 |
Li PKT, Chow KM, Cho Y, et al. ISPD peritonitis guideline recommendations: 2022 update on prevention and treatment[J]. Perit Dial Int, 2022, 42 (2): 110- 153.
doi: 10.1177/08968608221080586 |
| 3 | 中国腹膜透析相关感染防治专家组. 腹膜透析相关感染的防治指南[J]. 中华肾脏病杂志, 2018, 34 (2): 139- 148. |
| 4 |
Ma Y, Geng Y, Jin L, et al. Serum vancomycin levels predict the short-term adverse outcomes of peritoneal dialysis–associated peritonitis[J]. Perit Dial Int, 2023, 43 (1): 37- 44.
doi: 10.1177/08968608211064192 |
| 5 | 谢静, 张莹, 沈正泽. 万古霉素腹腔给药治疗腹膜透析相关性腹膜炎的血药浓度监测结果分析[J]. 中国医院用药评价与分析, 2024, 24 (7): 789- 792. |
| 6 |
杭永付, 徐德宇, 薛领, 等. 腹透相关性腹膜炎腹腔给予万古霉素血药浓度的特点及与疗效的关系[J]. 中国药学杂志, 2019, 54 (12): 1031- 1034.
doi: 10.11669/cpj.2019.12.019 |
| 7 |
何娜, 苏珊, 翟所迪, 等. 《中国万古霉素治疗药物监测指南(2020更新版)》解读[J]. 临床药物治疗杂志, 2021, 19 (1): 12- 16.
doi: 10.3969/j.issn.1672-3384.2021.01.003 |
| 8 | 蔡乐, 张庆涛, 谢大洋, 等. 腹膜透析相关腹膜炎患者万古霉素血药浓度监测结果分析[J]. 中国药物应用与监测, 2021, 18 (1): 13- 17. |
| 9 |
Stevenson S, Tang W, Cho Y, et al. The role of monitoring vancomycin levels in patients with peritoneal dialysis-associated peritonitis[J]. Perit Dial Int, 2015, 35 (2): 222- 228.
doi: 10.3747/pdi.2013.00156 |
| 10 | 辛洋洋, 阳晓. 腹膜透析标准化临床结局的研究进展[J]. 中华肾脏病杂志, 2023, 39 (8): 630- 634. |
| 11 | 董雪, 任天舒, 孙飞龙, 等. 腹膜透析相关性腹膜炎初始经验抗菌治疗方案研究[J]. 临床军医杂志, 2017, 45 (3): 300- 303. |
| 12 |
Dogan CZ, Kara E, Pinar A, et al. Therapeutic drug monitoring in patients treated with vancomycin: a single center, prospective, observational, real-world study[J]. Eur J Clin Microbiol Infect Dis, 2025, 44 (9): 2159- 2165.
doi: 10.1007/s10096-025-05182-w |
| 13 |
Deacon E, Canney M, McCormick B, et al. The association between serum vancomycin level and clinical outcome in patients with peritoneal dialysis associated peritonitis[J]. Kidney Int Rep, 2023, 8 (12): 2646- 2653.
doi: 10.1016/j.ekir.2023.09.013 |
| 14 |
袁世轩, 吕子彦, 杨勇, 等. 模型引导下的万古霉素血药浓度监测临床研究[J]. 中国临床药理学与治疗学, 2024, 29 (12): 1344- 1352.
doi: 10.12092/j.issn.1009-2501.2024.12.004 |
| 15 |
Blowey DL, Warady BA, Abdel–Rahman S, et al. Vancomycin disposition following intraperitoneal administration in children receiving peritoneal dialysis[J]. Perit Dial Int J Int Soc Perit Dial, 2007, 27 (1): 79- 85.
doi: 10.1177/089686080702700117 |
| 16 |
Liu W, Qiao Z, Xu Y, et al. Adjusting dialysis dose (Kt) scaled to body surface area (BSA) could be a more logical approach[J]. PLoS One, 2024, 19 (10): e0311175.
doi: 10.1371/journal.pone.0311175 |
| 17 | 王牡丹, 黄丽娃, 陈连国, 等. 腹透相关性腹膜炎患者血清万古霉素谷浓度与临床疗效的关系[J]. 中国现代医生, 2017, 55 (12): 9- 12. |
| 18 |
Terri M, Trionfetti F, Montaldo C, et al. Mechanisms of peritoneal fibrosis: focus on immune cells–peritoneal stroma interactions[J]. Front Immunol, 2021, 12, 607204.
doi: 10.3389/fimmu.2021.607204 |
| 19 |
Farkas A, Oikonomou K, Ghanbar M, et al. Population pharmacokinetics of intraperitoneal gentamicin and the impact of varying dwell times on pharmacodynamic target attainment in patients with acute peritonitis undergoing peritoneal dialysis[J]. Antimicrob Agents Chemother, 2022, 66 (2): e01679- 21.
doi: 10.1128/aac.01679-21 |
| 20 |
Bonomini M, Masola V, Monaco MP, et al. Coupling osmotic efficacy with biocompatibility in peritoneal dialysis: a stiff challenge[J]. Int J Mol Sci, 2024, 25 (6): 3532.
doi: 10.3390/ijms25063532 |
| 21 |
Geilen J, Kainz M, Zapletal B, et al. Effects of lung inflammation and injury on pulmonary tissue penetration of meropenem and vancomycin in a model of unilateral lung injury[J]. Int J Antimicrob Agents, 2024, 64 (1): 107180.
doi: 10.1016/j.ijantimicag.2024.107180 |
| 22 |
Chen Z, Taubert M, Chen C, et al. Plasma and cerebrospinal fluid population pharmacokinetics of vancomycin in patients with external ventricular drain[J]. Antimicrob Agents Chemother, 2023, 67 (6): e00241- 23.
doi: 10.1128/aac.00241-23 |
| 23 | 叶寅寅, 周茹, 宋霞, 等. 万古霉素血药浓度测定在腹膜透析相关性腹膜炎患者治疗中的作用[J]. 重庆医科大学学报, 2021, 46 (3): 350- 354. |
| 24 |
王敏, 邢玲玲, 张春霞, 等. 难治性腹膜透析相关性腹膜炎发生的影响因素及拔管风险预测[J]. 实用医学杂志, 2023, 39 (9): 1143- 1147.
doi: 10.3969/j.issn.1006-5725.2023.09.014 |
| [1] | 《三氧化二砷血药浓度监测中国专家共识》编写组. 三氧化二砷血药浓度监测中国专家共识[J]. 中国临床药理学与治疗学, 2026, 31(2): 185-195. |
| [2] | 刘媛, 崔诚, 余淼, 金文煜, 白银亮, 段雅彬, 方草, 贺建昌, 何艳, 黄桦, 霍仕霞, 金阳, 姜林, 姜哲, 焦正, 李学军, 李向阳, 李红健, 刘丽宏, 刘洋, 丘宏强, 孙凤, 孙建军, 王学昌, 王建华, 王振磊, 魏世杰, 颜晓文, 张雷, 张学农, 张宇馨, 赵军, 尹继业, 燕茹, 王新春, 刘东阳. 中国多民族人群精准用药研究价值与策略专家共识[J]. 中国临床药理学与治疗学, 2026, 31(1): 1-13. |
| [3] | 常钊, 周宇雪, 张胜男, 吕萌. 儿童肾病综合征患者他克莫司血药浓度变异性与临床疗效关系评价及影响因素分析[J]. 中国临床药理学与治疗学, 2025, 30(11): 1524-1529. |
| [4] | 石娟, 江琳, 马小鹏, 王静, 王教媛, 罗彬, 王婷婷. 乳腺癌患者自我隐瞒潜在剖面分析及影响因素研究[J]. 中国临床药理学与治疗学, 2024, 29(9): 1027-1034. |
| [5] | 周菊香, 李艳飞, 吕芳君, 李带田, 张继红, 伍继初. 伏立康唑血药浓度偏高的风险预测模型的构建[J]. 中国临床药理学与治疗学, 2024, 29(6): 653-660. |
| [6] | 袁世轩, 吕子彦, 杨勇, 陈璐, 张丽娟. 模型引导下的万古霉素血药浓度监测临床研究[J]. 中国临床药理学与治疗学, 2024, 29(12): 1344-1352. |
| [7] | 陶绍能, 葛俊亮, 杨继文, 陈晓磊, 尹惟礼, 王莹莹, 刘小岑. 分化型甲状腺癌术后首次131I治疗后疗效及影响因素分析[J]. 中国临床药理学与治疗学, 2024, 29(12): 1435-1440. |
| [8] | 肖雷, 曹灿, 刘加涛. 地高辛血药浓度和不良反应影响因素分析[J]. 中国临床药理学与治疗学, 2024, 29(11): 1280-1287. |
| [9] | 余巧玲, 翟葳葳, 刘 平, 邱 博, 吴惠珍. 利伐沙班血药浓度监测的研究进展[J]. 中国临床药理学与治疗学, 2023, 28(7): 809-817. |
| [10] | 王 鑫, 邬国栋, 安 明, 李 刚, 刘 洋. 文拉法辛相关PK-PD关系及影响因素研究进展[J]. 中国临床药理学与治疗学, 2023, 28(7): 788-795. |
| [11] | 钱 锦, 王峰岩. 老年急性心肌梗死患者PCI术后血清NT-proBNP水平的影响因素并分析其对近期预后的影响[J]. 中国临床药理学与治疗学, 2023, 28(6): 658-665. |
| [12] | 柳彤, 徐佳明, 王金伙, 尹磊, 陈永权, 郭建荣. 急性等容血液稀释自体血体外隔离期间血浆中麻醉药物浓度变化及回输后对麻醉效应的影响[J]. 中国临床药理学与治疗学, 2023, 28(4): 413-418. |
| [13] | 吴莉莉, 梁 至, 黄思咏, 王 妍. 肾功能亢进对感染性心内膜炎患者万古霉素药动学的影响及有效性与安全性研究[J]. 中国临床药理学与治疗学, 2023, 28(10): 1139-1145. |
| [14] | 杜文鹏, 敖检根, 陶 祎, 吴观胜, 何佳珂. 自身免疫疾病患者他克莫司稳态血药浓度影响因素的研究[J]. 中国临床药理学与治疗学, 2022, 27(6): 645-651. |
| [15] | 胡殷, 杨丹丹, 徐毅超, 邵蓉, 阮邹荣, 江波, 陈金亮, 楼洪刚. 人工神经网络模型在坎地沙坦酯片生物等效性研究中的应用[J]. 中国临床药理学与治疗学, 2022, 27(1): 63-69. |
| 阅读次数 | ||||||
|
全文 |
|
|||||
|
摘要 |
|
|||||



